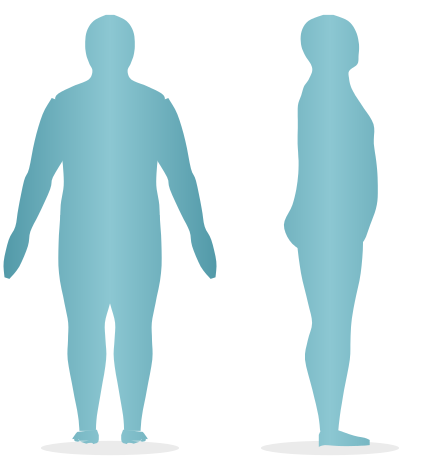
 BMI 26
 BMI 28
 BMI 32
 BMI 34
What Does a BMI 30 Male Body Look Like?
A man at BMI 30 has crossed the clinical threshold into obesity, and this is reflected visually in a body shape that is unmistakably heavy. The abdomen dominates the silhouette. Viewed from the side, the stomach extends well forward of the chest and hips, forming a prominent rounded protrusion. From the front, the midsection is wide and barrel-shaped. The gut is not just soft but substantial in volume, consistent with the significant visceral fat that drives both the appearance and the health risks at this BMI.
Love handles are large and distinct — well-developed rolls of fat on the lateral abdomen that are visible even through loose-fitting clothing. The lower back carries a band of fat that raises the apparent waistline visually. The buttocks are rounded and fleshy. The hips and upper thighs may also carry fat deposits, though in men the predominant storage remains central and abdominal.
The neck is thick and the throat is full. A pronounced double chin is visible from most angles, particularly when the head is level or tilted downward. The cheeks are round, and the face has lost the jawline definition typical of leaner body weights. The jowls may begin to sag in older men.
Clothed appearance: dress shirts and formal jackets must be bought in a larger size than shoulder measurements alone would suggest. The waistband of trousers has increased substantially — many men at BMI 30 find that their trouser waist size (typically 38–42 inches) is considerably larger than their chest size for the first time in their lives. The distinction between the "gut" and the rest of the body is clearly visible even in loose-fitting jumpers or t-shirts.
Physical performance is meaningfully impaired. Aerobic capacity is reduced relative to lean body weight because the cardiovascular and respiratory systems must work harder to supply a body approximately 16 kg heavier than healthy weight (95.1 kg vs 78.9 kg at 178 cm). Climbing stairs, sustained walking, and physical labour become noticeably harder and are associated with faster breathing and quicker fatigue.
It is worth noting that a very muscular man — a competitive powerlifter or rugby player with high lean mass — might technically reach BMI 30 without appearing obese in the conventional sense. However, for the average sedentary or moderately active British man, BMI 30 presents as described above, and the health risks are very real regardless of subjective appearance.
Health Risks of BMI 30 for Men
Crossing the BMI 30 threshold has meaningful clinical significance. Obesity Class I is associated with a substantially elevated burden of chronic disease, reduced life expectancy, and impaired quality of life. The WHO estimates that overweight and obesity account for approximately 4 million deaths annually worldwide.
Type 2 Diabetes
Obese men have approximately double the risk of developing type 2 diabetes compared to healthy-weight men. Visceral fat directly drives hepatic insulin resistance through the portal circulation, impairing glucose regulation. Many men who reach BMI 30 will already have impaired fasting glucose or pre-diabetes. A fasting glucose or HbA1c test is strongly advised.
Cardiovascular Disease
Obesity increases the risk of coronary artery disease, heart failure, and stroke. The mechanisms are multiple: hypertension (driven by increased cardiac output and sodium retention), atherogenic dyslipidaemia (elevated triglycerides, reduced HDL, increased small dense LDL), chronic systemic inflammation, and direct lipid deposition in coronary arteries. At BMI 30, blood pressure is typically 8–15 mmHg above healthy-weight baseline.
Waist Circumference
Men at BMI 30 typically have a waist circumference of 99–108 cm — firmly in or above the NHS high-risk zone (≥102 cm). Waist above 102 cm in men is associated with significantly elevated risk of all-cause mortality independent of BMI. Reducing waist below 94 cm is a primary clinical target.
Testosterone and Hormones
Men at BMI 30 have meaningfully suppressed testosterone levels — typically 15–25% below age-matched healthy-weight men. Aromatase in visceral fat converts testosterone to oestradiol, and elevated adipokines (leptin, resistin) directly suppress hypothalamic GnRH pulsatility. Clinically, this may manifest as low libido, reduced energy, impaired muscle growth, and subclinical hypogonadism. Weight loss reliably and substantially raises testosterone in obese men.
Sleep Apnoea
Obstructive sleep apnoea (OSA) affects an estimated 30–50% of obese men. Fat deposits in the neck and parapharyngeal tissues narrow the upper airway, causing repeated partial or complete airway obstruction during sleep. This fragments sleep architecture, reduces oxygen saturation, and dramatically increases cardiovascular risk. If you snore loudly, wake gasping, or feel chronically unrefreshed, request a sleep study from your GP.
Cancer Risk
Obesity at BMI ≥30 is associated with increased risk of multiple cancers, with the strongest evidence for colorectal, kidney, oesophageal (adenocarcinoma), and pancreatic cancers in men. The mechanisms include chronic insulin/IGF-1 elevation, adipokine signalling, and local inflammation.
Getting from BMI 30 to a Healthy Weight
To reach a healthy BMI of 24.9 at 178 cm requires reaching approximately 78.9 kg — a reduction of 16.2 kg from 95.1 kg. This is a substantial but entirely achievable goal. However, it is important to know that significant health improvements occur well before reaching this target.
A 5–10% weight reduction (approximately 4.8–9.5 kg) produces clinically meaningful improvements in:
- Blood pressure (typically down 5–10 mmHg systolic)
- Fasting blood glucose and insulin sensitivity
- Triglycerides and HDL cholesterol
- Testosterone levels
- Sleep quality and sleep apnoea severity
- Joint pain and mobility
Diet
The evidence base for obesity management supports structured energy deficit approaches: total energy intake of approximately 1,600–1,800 kcal/day for most men, emphasising high protein (≥1.6 g/kg), fibre-rich vegetables, and reduced ultra-processed food. Low-carbohydrate diets (targeting 50–130 g carbs/day) show particular effectiveness for visceral fat reduction and glycaemic control. VLCD (very low calorie diet, 800 kcal/day) under medical supervision can achieve 1–1.5 kg/week loss.
Exercise
150–300 minutes of moderate-intensity physical activity per week is the evidence-based target for weight management. Combining resistance training (3×/week) with structured cardio (walking, cycling, swimming) produces superior body composition outcomes. Resistance training is particularly important for men as it preferentially reduces visceral fat and counteracts testosterone suppression from adipose aromatase.
Clinical Options
Men with BMI ≥30 may qualify for NHS weight management services including tier 2 community programmes, tier 3 specialist services, and potentially pharmacotherapy (e.g., GLP-1 receptor agonists). Men with BMI ≥35 with comorbidities may meet eligibility criteria for bariatric surgery. Speak to your GP to understand what support is available.
BMI 30 male: weight for every height
The weight that gives a BMI of 30 depends on height. The highlighted row is the 178 cm reference height used for the images on this page.
| Height | Kilograms | Stones | Pounds |
|---|---|---|---|
| 5ft 4in (163 cm) | 79.3 kg | 12 st 7 lb | 175 lb |
| 5ft 5in (165 cm) | 81.8 kg | 12 st 12 lb | 180 lb |
| 5ft 6in (168 cm) | 84.3 kg | 13 st 4 lb | 186 lb |
| 5ft 7in (170 cm) | 86.9 kg | 13 st 10 lb | 192 lb |
| 5ft 8in (173 cm) | 89.5 kg | 14 st 1 lb | 197 lb |
| 5ft 9in (175 cm) | 92.1 kg | 14 st 7 lb | 203 lb |
| 5ft 10in (178 cm) | 94.8 kg | 14 st 13 lb | 209 lb |
| 5ft 11in (180 cm) | 97.6 kg | 15 st 5 lb | 215 lb |
| 6ft 0in (183 cm) | 100.3 kg | 15 st 11 lb | 221 lb |
| 6ft 1in (185 cm) | 103.1 kg | 16 st 3 lb | 227 lb |
| 6ft 2in (188 cm) | 106.0 kg | 16 st 10 lb | 234 lb |
| 6ft 3in (190 cm) | 108.9 kg | 17 st 2 lb | 240 lb |
| 6ft 4in (193 cm) | 111.8 kg | 17 st 8 lb | 246 lb |
| 6ft 5in (196 cm) | 114.8 kg | 18 st 1 lb | 253 lb |
| 6ft 6in (198 cm) | 117.8 kg | 18 st 8 lb | 260 lb |
How far is BMI 30 from a healthy weight?
At 178 cm, BMI 30 is 95.1 kg (15 st 0 lb). The top of the healthy range at this height is 78.9 kg (12 st 6 lb), so reaching a healthy BMI would mean losing about 16.2 kg (2 st 8 lb). BMI 30 sits right on the boundary of this category, so losing even 1 kg would move you back into the one below.
You do not need to get all the way there to feel the benefit. A 5% loss is 4.8 kg and a 10% loss is 9.5 kg; both are linked with lower blood pressure and blood sugar. At a steady 0.5 kg a week, 5% would take about 10 weeks and reaching the healthy range about 32 weeks.
What the NHS and NICE suggest at BMI 30
A BMI of 30 to 34.9 is classed as obesity (class 1). It significantly raises the risk of type 2 diabetes, heart disease, some cancers, sleep apnoea and joint problems.
Your GP can talk through your options and may refer you to a local weight management service, which offers group or one-to-one support with diet, activity and behaviour. For some people with weight-related conditions, NICE-recommended weight-loss medicines may also be considered as part of a wider plan. The free NHS Weight Loss Plan app is a good place to start.
With NICE’s lower thresholds for people of South Asian, Chinese, other Asian, Middle Eastern, Black African or African-Caribbean background, each obesity class starts 2.5 points lower, so BMI 30 is treated as class 1 obesity.
Whatever your BMI, measure your waist. At 178 cm, a waist under 89 cm (35 in) means a healthy waist-to-height ratio. Between 89 and 107 cm the risk is increased, and above 107 cm it is high.
Sources
The body shapes on this site are illustrations generated from height, weight and sex. They show a typical build and cannot show your own muscle, frame or fat distribution. BMI is a screening measure for adults aged 18 and over; it is not a diagnosis and is not valid during pregnancy. Speak to your GP or a registered dietitian for personal advice. Full disclaimer.